16 Things Medicare Counselors Wish You Knew Before You Signed Up
Medicare counselors see the same costly mix-ups over and over, and most of them trace back to a rule nobody explained clearly beforehand.
By Linda Cho, CFP®, Money Editor
Updated · 16 min read
- Written by our money editor
- How we review

A counselor at a county aging office once said the saddest calls are never about confusing paperwork. They are about a rule someone would have followed easily, if only they had heard it before the deadline instead of after.
That gap between what counselors know and what gets explained at sign-up is where real money and real coverage slip away. Below are the warnings they wish landed earlier, straight from the guidance issued by Medicare, Social Security, and the tax agencies that quietly govern how all of this works.
1The Three-Day Rule Can Sink Your Nursing Home Coverage

Hospitals sometimes keep patients for tests and monitoring without ever formally admitting them. That status feels identical from the bed, same room, same gown, same beeping monitors, but it counts differently on paper. The label the hospital chooses behind the scenes decides what happens next.
Only time spent as a formally admitted inpatient builds toward the qualifying stay that nursing home coverage requires. Time spent under observation, no matter how long, does not count toward that stay. Families often discover this only after the nursing facility bill arrives.
Ask the hospital directly, in plain language, whether your stay is inpatient or observation, and ask again each day. Get the answer in writing if you can. If the label seems wrong, ask the case manager to review it before discharge, not after.
2The Part B Penalty Never Goes Away

Most people assume a missed deadline means a temporary fine, something that fades after a year or two of good behavior. Part B does not work that way. The penalty attaches to the premium itself and rides along for as long as the premium exists.
Every full period without coverage after your enrollment window passed adds another fixed slice on top. The math is not forgiving and there is no cap that kicks in later to soften it. Someone who waited several years can end up paying substantially more than a neighbor who signed up on time.
Treat the enrollment window as final, not flexible. If you already missed it, ask a counselor whether an exception applies before assuming the penalty is permanent. Otherwise, plan your retirement budget as though this extra cost is staying for good.
3The Part D Penalty Is Calculated a Different Way Than Most People Think

People assume a drug plan penalty grows the way their own premium grows, slowly and predictably. It does not. The number behind the Part D penalty is tied to a national average premium that Medicare recalculates every year, not the plan the person actually bought.
That average can rise even while a person's chosen plan stays flat or gets cheaper. The penalty is a percentage of that shifting national figure, so the dollar amount attached to an old gap in coverage can quietly climb over time. Nobody has to do anything wrong for that to happen.
Do not assume an old penalty is locked at the size it was the year it was assessed. Check your annual notice of change each fall. If the number looks different from last year, that is expected, not a billing mistake.
4There's a Six-Month Window Where Insurers Can't Say No

Signing up for Part B starts a countdown that most people never hear about until it matters. During this window, private insurers selling supplemental coverage have to accept you. They cannot ask about your health history and they cannot charge you more because of it.
This protection exists because Medigap insurers, unlike Advantage plans, are generally allowed to medically underwrite applicants outside this stretch of time. The window gives every new enrollee one guaranteed shot at buying coverage on equal footing with everyone else applying that month.
Mark the date your Part B coverage begins and count forward. Apply for any supplemental policy well inside that stretch, not at the edge of it. Waiting until the final days leaves no room for paperwork delays or a denied application to be fixed in time.
5After That Window Closes, You Can Be Turned Down

Once the guaranteed window closes, the rules flip in the insurer's favor. In most states, a company can review your health history before deciding whether to sell you a policy. It can also decide what to charge you based on what it finds.
This is not a rare technicality. People with ongoing health conditions are the ones most likely to get declined or quoted a much higher rate, which is precisely backward from what they need. A clean bill of health at the wrong moment becomes the deciding factor.
Never let a supplemental policy lapse assuming you can simply buy a new one later on the same terms. If you are shopping outside your guaranteed window, ask directly whether the insurer is underwriting your application. A few states offer extra protections, so ask a local counselor what applies where you live.
6Your Premium Is Based on Income From Two Years Ago

The premium notice that arrives can feel disconnected from your current finances, and that is because it is. Medicare sets higher premiums for Part B and Part D using a tax return filed a couple of years earlier, not your income right now.
Someone who just retired and dropped to a fixed income can still get billed as though they were earning their old salary. The lag is built into the system on purpose, since that is the most recent verified tax data the government has on file.
Do not assume a high premium notice reflects a mistake simply because your current income looks nothing like it. Check which tax year the notice cites before calling to dispute anything. Knowing the lookback year in advance saves a frustrating call to a representative who is only following the file.
7A Life Change Can Undo That Surcharge

A surcharge based on old income sounds like something you simply have to absorb, but it is not always final. Medicare allows people to report specific life changes that make an old tax return an unfair basis for the current premium.
Retirement itself is one of the recognized triggers, along with a handful of other major shifts in work or household income. There is a specific form built for exactly this appeal, and it asks for documentation of the change rather than a general complaint about affordability.
If your income dropped for a documented reason, file that form instead of paying the higher premium and hoping it corrects itself. Bring proof of the life event, such as a retirement letter. A local counselor can tell you whether your situation qualifies before you submit anything.
8Every Plan Gets a Public Report Card

Every Medicare Advantage and Part D plan on the market gets scored every year on a simple public scale, and almost nobody looks at it before enrolling. The score reflects things like member complaints, customer service performance, and how well the plan manages chronic care.
A plan that looks appealing based on premium and drug list alone can still have a poor track record on service and outcomes. That history is measured, published, and updated annually, not hidden behind marketing language on a brochure.
Look up the current score for any plan before you sign anything, not after. A pattern of low scores across several years is a stronger warning sign than one bad year. Treat the score as one more piece of evidence, alongside cost and coverage.
9Free, Unbiased Counseling Is Already Paid For

People assume good Medicare advice has to come from an agent who earns something from the sale. It does not. Every state runs a counseling program, funded through the federal government, staffed by trained volunteers and employees who have no financial stake in what you choose.
These counselors will not sell you anything, will not steer you toward a particular company, and will not take a commission based on the plan you pick. Their entire purpose is to walk through your specific situation and explain the tradeoffs plainly.
Call your local program before meeting with any agent, especially if you feel confused or pressured. Bring a list of your medications and doctors to make the session useful. There is no cost to the appointment and no obligation afterward.
10Missing Your Window Doesn't Mean Missing Medicare Forever

A missed deadline feels like a locked door, but Medicare keeps a separate window open every year specifically for people who did not sign up when they were first eligible. It falls early in the calendar and it exists on a fixed, predictable schedule.
Coverage that starts through this later window does not begin the day you apply. There is a gap between enrolling and the date benefits actually kick in, which matters if you are relying on that coverage for a procedure or ongoing treatment.
Mark this window on your calendar the moment you realize you missed your original deadline. Apply as early in the window as possible to shorten the wait before coverage starts. A penalty may still apply, but coverage itself is not lost permanently.
11Losing Job Coverage Starts an Eight-Month Clock

Leaving a job, or losing the health coverage that came with it, starts a countdown that catches a surprising number of people off guard. The clock begins the moment either the employment or the coverage tied to it ends, whichever happens first.
People sometimes assume the countdown starts when they decide to enroll, or when they finally get around to the paperwork. It does not work that way. The trigger is the loss of coverage itself, not any later action the person takes.
Write down the exact date your job coverage ended, not the date you noticed. Start the enrollment process well before the window closes rather than near the end. Waiting too long here can create the same lasting penalty that missing the original window creates.
12The Size of Your Employer Changes the Rules

Two people can retire from very different companies and end up under completely different coverage rules, simply because of how many people their employer employed. That single fact decides whether Medicare or the employer's insurance pays first once someone is eligible for both.
At a smaller employer, Medicare typically becomes the primary payer, which changes how and when someone should enroll. At a larger employer, the workplace plan often stays primary, which changes the calculation entirely for whether delaying Part B makes sense.
Ask your benefits office directly how many employees the company has, not how it feels to work there. Confirm which payer is primary before deciding to delay any part of Medicare. Getting this backward can leave real medical bills unpaid by either side.
13Advantage Plans Have a Legal Spending Ceiling

Original Medicare has no built-in limit on how much a person might pay out of pocket in a bad year. A serious illness or injury can generate costs that simply keep accumulating with no government-mandated stopping point.
Medicare Advantage plans work differently by law. Every one of them is required to include a ceiling on in-network out-of-pocket spending each year, after which the plan covers the rest of the covered care for the remainder of that year.
Ask any Advantage plan you are considering what its current ceiling is and whether it differs for out-of-network care. Compare that number against your own tolerance for financial risk. This single protection is often the deciding factor for people choosing between the two paths.
14The Same Letter Means the Same Benefits, Everywhere

Supplemental policies are organized by letter, and that letter carries real legal weight. A policy labeled with a particular letter has to cover the exact same set of benefits no matter which insurance company is selling it or what state you buy it in.
This surprises people who assume a fancier-sounding company must be offering something better. The coverage itself cannot legally differ. What varies from company to company is entirely on the business side, not the medical benefits side.
Once you know which letter fits your needs, stop comparing benefits between companies, since they are identical by law. Spend your comparison time on premium, customer service reputation, and rate history instead. That is where the real differences actually live.
15Two People With the Same Plan Can Pay Very Different Premiums

Two neighbors can hold the identical supplemental policy, same letter, same benefits, and still pay very different amounts. The gap comes from the pricing method the insurer chose, and each company picks its own approach when it builds the policy.
Some insurers price everyone at the same rate within a group regardless of age. Others price strictly by the age you were when you bought the policy. A third approach reprices you as you get older, so the bill climbs steadily every year you keep the policy.
Ask any insurer directly which pricing method their policy uses before comparing premiums across companies. A cheaper starting premium under an age-based method can end up costing far more over time. Request the full pricing structure in writing, not just the current-year quote.
16The Donut Hole Closed, but a New Number Took Its Place

For years, a well-known coverage gap forced many people to pay a much larger share of drug costs for a stretch in the middle of the year. That gap has been eliminated under a federal law that reshaped how drug spending is structured.
In its place, a hard annual ceiling now caps what an individual pays out of pocket for covered prescription drugs. Once spending reaches that ceiling within the year, covered drug costs for the rest of the year stop falling on the patient.
Track your own drug spending against the current ceiling rather than assuming the old gap rules still apply. Ask your pharmacist or plan for a running total during the year. Knowing where you stand against that ceiling helps you plan for expensive months ahead.
17A Program Can Erase Most of Your Drug Costs

Many people assume help with drug costs is only for those with almost no income or savings at all. The actual thresholds for the federal Extra Help program are more generous than most people expect, and plenty of solidly middle-income retirees qualify.
The program reduces premiums, lowers or eliminates deductibles, and caps what a person pays for each prescription at a low, fixed amount. It applies automatically to some people already receiving certain other benefits, but many eligible people never apply because they assume they will not qualify.
Apply through the Social Security Administration even if you are unsure whether your income and savings fit. The application itself costs nothing and does not lock you into anything. A denial does not follow you or affect any other benefit.
18A State Program Can Pay Your Part B Premium

Part B premiums get deducted automatically for most people, which makes them feel unavoidable. For people within certain income and asset limits, a state-run Medicare Savings Program can pay that premium directly, and in some cases pick up other cost-sharing too.
These programs go by specific names that vary somewhat state to state, and the income cutoffs are tied to federal poverty guidelines that get updated periodically. Many people who qualify never apply because they assume savings programs are only for people on other forms of public assistance.
Contact your state Medicaid office or local counseling program to ask which savings program applies where you live. Bring recent statements of income and assets to the appointment. Being turned down once does not mean you would be turned down again after a change in circumstances.
19Most People Give Up at the First Level of Appeal

A denied claim feels final, and most people treat it that way, quietly paying the bill or giving up on the service altogether. In reality, that denial is only the first step of a formal process with several more levels built specifically for disagreements like this.
Each level has its own deadline for filing and its own reviewer, moving from the plan itself up through independent reviewers and eventually a formal hearing. Very few denials get challenged past that very first step, even though later levels reverse a meaningful share of them.
Read the denial notice for the exact deadline to move to the next level and mark it immediately. Keep every document related to the claim in one folder from the start. A counselor can help you draft the appeal even if you have never challenged a decision before.
20Your HSA Contributions Have to Stop the Month You Enroll

Health savings accounts and Medicare do not mix the way people assume they will. The moment Part A coverage begins, contributions to a health savings account are no longer allowed to be tax deductible, even if the person is still actively working and covered by a high-deductible plan.
The complication most people miss is that Part A enrollment can be backdated when someone signs up later than their initial window. That backdating can retroactively make contributions from earlier months improper, creating a tax problem the person never saw coming.
Stop contributing to a health savings account well before you expect Medicare coverage to begin, not on the date it actually starts. Talk to a tax professional about the backdating rules before enrolling if you have delayed signing up. Cleaning this up before filing taxes is far easier than after.
21Delaying Social Security Doesn't Delay Medicare

People who plan to wait on Social Security to grow their monthly benefit sometimes assume Medicare will simply wait along with it. The two programs are administered separately, and enrolling in one does not automatically enroll a person in the other.
For most people, Medicare enrollment still has to happen around the same age regardless of whatever decision they have made about claiming Social Security. Skipping this step because Social Security is being delayed is one of the more common and costly mix-ups counselors see.
Set a reminder tied to your own birthday, not to whatever Social Security decision you are planning. Enroll in Medicare on that schedule even if your Social Security benefit will not start for years. Treat the two decisions as entirely separate paperwork, because that is exactly what they are.
22The Official Comparison Tool Resets Every Fall

The government's own plan comparison tool is one of the more reliable resources available, but it has a quirk that trips people up. The plan details, pricing, and drug coverage information get refreshed on a set annual schedule tied to the fall enrollment season.
Information a person looked at earlier in the year, or saved from a previous year's research, may no longer reflect what a plan actually offers once the refresh happens. Screenshots and printed comparisons from an old cycle can be quietly out of date without any obvious warning.
Always pull a fresh comparison during the current enrollment season rather than relying on notes from a previous year. Bookmark the tool itself rather than a saved page of results. Treat any comparison older than one enrollment cycle as unreliable until you have rechecked it.
23Two Plans Can Cover the Same Drug Under Different Rules

Two plans can both list the exact same medication as covered, yet make it far harder to actually get through one plan than the other. The difference comes down to extra rules attached to that drug, which vary by plan even when the drug list looks identical.
Some plans require prior authorization, meaning a doctor has to justify the prescription before the plan will pay. Others require step therapy, meaning a patient has to try and fail a cheaper drug first. These rules are documented in each plan's official filings, not hidden.
Before assuming a drug is fully covered, check whether the plan attaches prior authorization or step therapy requirements to it. Ask your doctor's office whether they have dealt with that specific plan before. A drug being listed as covered is not the same as a drug being simple to get.
24There's a Second Switching Window Early in the Year

Most people know about the long switching window that runs in the fall, but there is a second, narrower one that only applies to people already enrolled in an Advantage plan. It falls early in the calendar year, well after the fall window has closed.
This window allows exactly one additional switch, either to a different Advantage plan or back to Original Medicare, but it is not open to everyone. People who started the year in Original Medicare do not get to use it to switch into Advantage.
Mark your calendar for this early window if you enrolled in an Advantage plan during the fall and have second thoughts. Use it only once, since a second switch within the same window is not allowed. Ask a counselor to confirm your eligibility before assuming this option applies to you.
25A Hospital Can Call You a Patient Without Admitting You
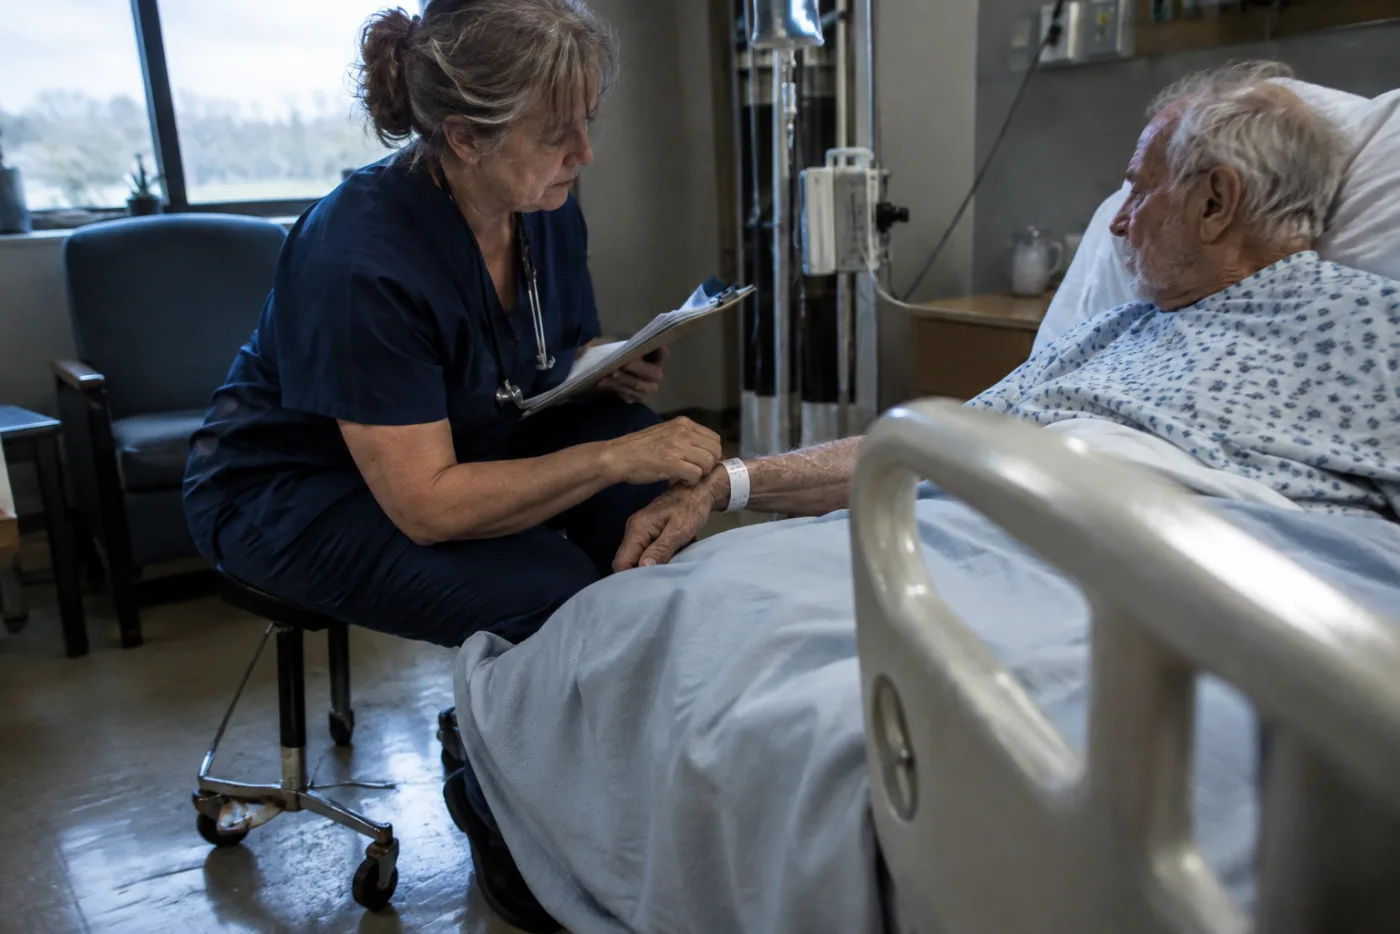
A hospital stay can look identical from the inside whether or not a person has been formally admitted, which is exactly why hospitals are required to give written notice explaining the difference. That notice spells out, in plain language, whether the stay counts as observation.
The label matters because it changes what Medicare will pay for afterward, particularly around nursing home coverage. Patients frequently assume that because they were kept overnight, or for several nights, they must have been admitted, and that assumption is often wrong.
Read the notice the hospital gives you as soon as it arrives, not after discharge. Ask directly whether your status has changed at any point during the stay, since it sometimes shifts partway through. If something about the label seems off, raise it with the case manager immediately.
26Your Deductible Can Reset Twice in the Same Year

People assume a deductible is a once-a-year event, paid and then done with until the calendar flips. Original Medicare's hospital deductible does not work on a calendar year at all. It is tied instead to something called a benefit period, which resets based on gaps in care, not dates.
A new benefit period begins after a person has been out of the hospital and out of a skilled nursing facility for a defined stretch of time. If a new hospital stay happens after that gap, it can trigger an entirely new deductible, even though the calendar year has not changed.
Ask the hospital or a counselor whether a new stay falls inside your current benefit period or starts a fresh one. Do not assume a deductible paid earlier in the year covers a later, unrelated hospital stay. Two stays with a long enough gap between them can mean paying that deductible twice.
The bottom line
None of this is designed to be confusing on purpose. It is simply spread across different agencies, different notices, and different deadlines that never talk to each other. Counselors spend their careers connecting those dots. Now you have a head start on the conversation before you sign anything.
Linda Cho, CFP®
Money Editor
Linda is a certified financial planner who spent two decades advising retirees before joining Prime Journal.
Get our Sunday email
Our best finds of the week. Free.
Most read
You might also like


